Run one study on the full Horizon + Bridge engine for $1,200/mo. The complete recruitment package plus community outreach. No management fee, no ad-spend markup, and $300 toward your first month of ad spend. Pilot offer
Paid ads only find the patients already searching. Bridge reaches the rest — through the advocacy groups, community clinics and provider networks that already serve your study population — and turns them into a compliant referral engine for your trial.
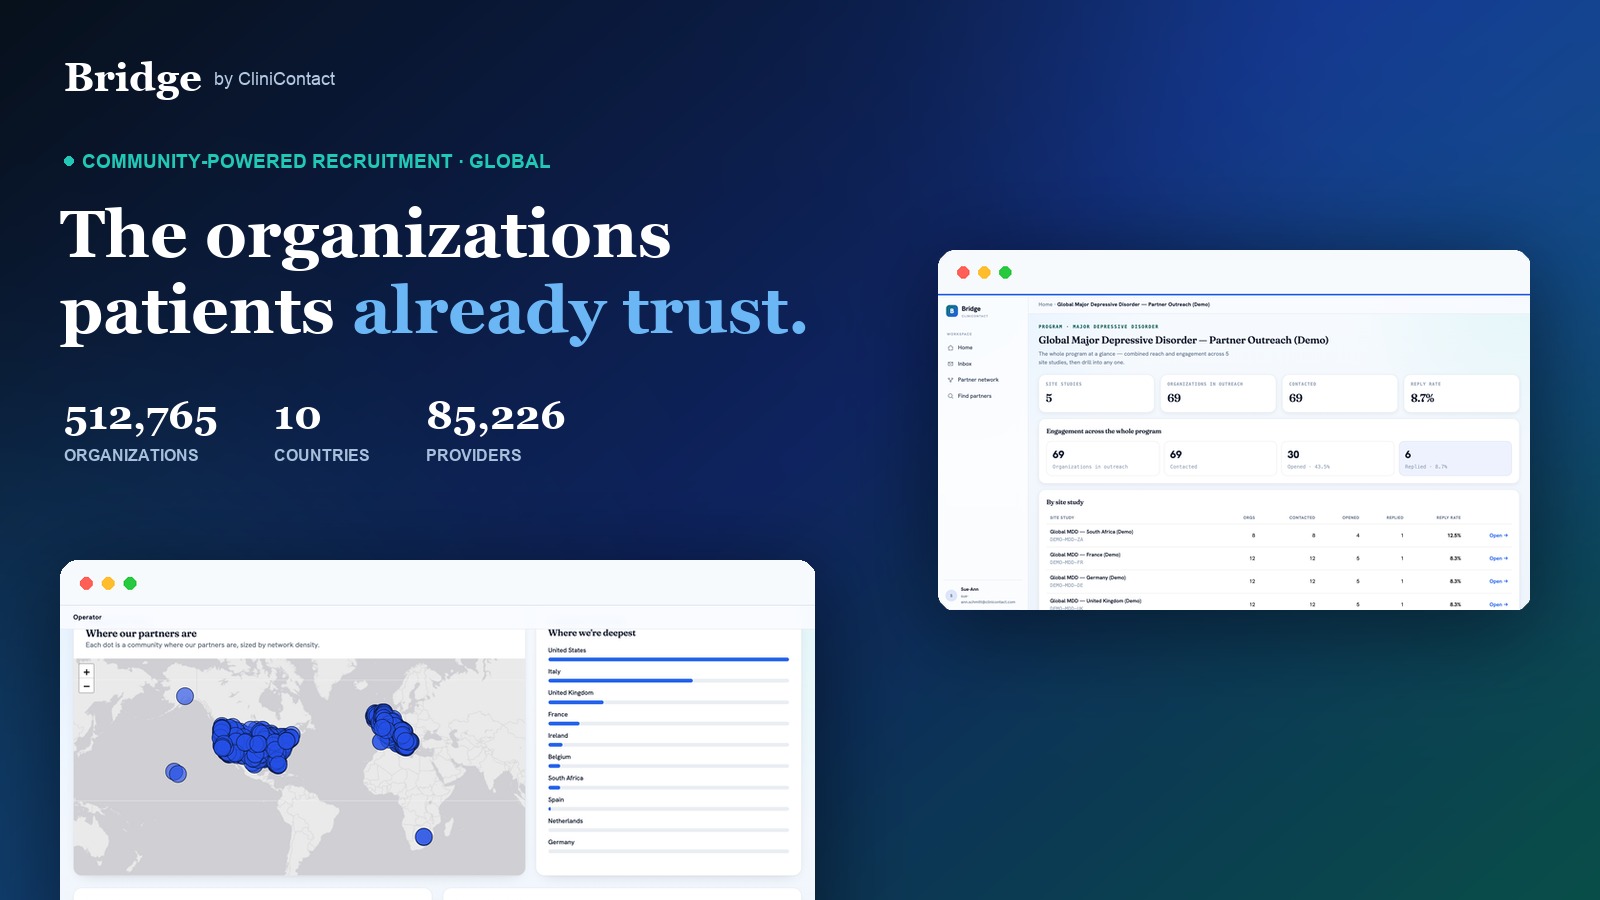
A living map of relationships with the organizations that reach real patients — mapped, verified and remembered across studies, so your next trial starts warm.
Live registry counts as of Sep 2026 · 442,741 confirmed trial-relevant · 80,177 mapped to a specific condition. Operators see the always-live footprint in the dashboard.
The global network your study plugs into, and the client portal where you watch it work — both live, both yours.
The global map, reach by condition, the communities served, and country-level census depth.
Your programs at a glance, outreach health scored and explained, and every named partner behind each study.
Page through a full strategy Bridge produced.
A real (demo) plan end to end: funnel, reach, partner channels, catchment map and the six-month program.
Clinical trials have a reach problem. The people who could benefit most — families facing a rare diagnosis, patients in rural towns, communities research has long overlooked — are too often the last to hear that a study even exists.
Bridge changes who gets asked. Instead of cold ads, we reach people through the advocacy groups, clinics and community leaders they already know. When an invitation comes from someone you trust, it lands differently, and doors that used to stay closed start to open.
It is also how a Diversity Action Plan gets carried out, not just filed.
We meet patients where they already are, through organizations that earned their community's trust over years, not overnight.
Rural, underserved and historically excluded communities get a real seat at the table, not an afterthought once enrollment stalls.
Every referral is someone's mother, son or neighbor — getting a chance they might never have heard about otherwise.
Built to reach patients through the people and organizations they already trust — from finding the right partners to a warm referral in your portal.
We pinpoint the advocacy groups, clinics, provider networks and community organizations that already reach your study population — matched to your indication and catchment, and carefully curated so outreach is targeted, never spam.
We engage partners the way they actually connect: email, social and professional networks — with respectful, fully compliant, opt-out-friendly messaging that never over-contacts one organization.
Every reply gets a real response. Interested partners are guided to refer patients to the right study, and each relationship is kept warm across the whole organization.
A clean, patient-friendly study finder helps interested people find the right study and next step by condition and location — the trusted entry point for community referrals.
Running one indication across many sites? We engage the community once and connect each interested patient to their best-fit site, with a single rolled-up view across the whole program.
Log in any time to watch engagement, referrals and your community footprint update in real time — progress you can see unfold, not a weekly status deck.
However you run trials, Bridge adds the community-referral channel that paid media can't reach — scoped to how you work.
Carry out your Diversity Action Plan for real, reaching the communities paid media misses — with a referral trail you can put in front of the FDA.
Add a community-referral channel to any protocol you run. Flat-fee, priced to compound down across a portfolio, and something you can name in the bid.
Feed every site a warm, pre-qualified referral stream from the advocacy groups and clinics around it — one indication engaged once, routed to the best-fit site.
Run real community outreach for an investigator-initiated study without standing up a recruitment team — from a single indication to a whole department.
Every market maps to its own networks and rules — US community health centers and FQHCs, UK NHS trusts and disease charities, EU patient organizations, South African community networks — with catchment demographics from official census sources and outreach aligned to each region's research-ethics and privacy standards.
Types of partners
How the network is built
Each market is measured against its own official census metric, so the number means what the regulator in that region means by it.
from under-represented groups · vs 42.6% baseline
US Census Bureau · ACS (B03002)
ethnic-minority residents · vs 18.3% baseline
ONS · Census 2021 (TS021)
foreign-born residents · vs 13.4% baseline
Eurostat · 2023
from historically under-represented groups
Statistics South Africa · Census 2022
This is what turns a Diversity Action Plan into something you can evidence, not just state.
Conditions and specialties worked across
A real count of the registered patient organizations and health charities Bridge can mobilize across the conditions the model is built for. Every figure is a live directory count, shown here for the two deepest markets.
Depression, Alzheimer's, Parkinson's, epilepsy, MS, ALS, schizophrenia, Huntington's
Breast cancer, multiple myeloma
Sickle cell disease, cystic fibrosis
Lupus, rheumatoid arthritis
We build an indication-level partner profile: the org types, specialties and geographies that reach your population.
We build a targeted, vetted list of the organizations and people who genuinely fit your study. Quality over quantity, no spam lists.
We reach out respectfully across the right channels, respond to every reply, and help interested partners refer patients to the right study.
Track engagement, referrals and the community footprint live in your client portal.
CliniContact runs two recruitment engines that share one participant record. Most studies use both: Horizon reaches the patients who are searching, Bridge reaches the ones who are not.
Give Horizon a protocol link or PDF, and about an hour later you have the full recruitment package and a study-specific marketing strategy, screened for IRB and platform compliance. Then we build and run the digital ad campaigns, tuned weekly to cost-per-qualified-candidate.
The community-outreach engine on this page. Bridge reaches patients through the advocacy groups, clinics and communities that already serve them, and turns those relationships into a compliant referral pathway — built to evidence a Diversity Action Plan.
One participant record across both, so a lead from a Facebook group and a lead from a paid ad land in the same place, screened the same way.
One indication covers every study you run in it. Bridge is priced by how hard the community is to reach, and nothing else. No management fee, no markup.
High-prevalence conditions with broad advocacy and community networks already in place.
Specialized communities with fewer, harder-to-find partners, and more field-building to open the pathways.
Ultra-low prevalence and tightly concentrated communities, where every partner counts.
No management fee · No ad-spend markup · No per-seat or setup fees
Minimum term: Horizon 3 months, Bridge 6 months. Community outreach needs the runway to build partner relationships.
Running several indications or a site network? Request a full quote →
Most vendors buy lists or run more ads. Bridge builds real relationships with the organizations a community already trusts, then turns interest into vetted referrals. Nothing is spam, every reply gets a human response, and each relationship is remembered across studies.
No. Bridge engages organizations — advocacy groups, clinics, provider networks. They share the study with the people they serve, and interested patients come to a clean study finder on their own terms. Individual contact details stay with the outreach team, never the client.
Yes. Messaging is respectful, opt-out-friendly and never over-contacts one organization, and it is aligned to each market's research-ethics and privacy standards — FDA/IRB and HIPAA in the US, HRA/REC and UK GDPR in the UK, and the equivalents across the EU and South Africa.
Bridge reaches under-represented communities through the organizations that already serve them, and every referral leaves a trail. That turns a Diversity Action Plan from something you file into something you can evidence — with real reach into the communities paid media misses.
Yes. Bridge is a standalone community-outreach engine. Most studies run it alongside Horizon so paid and community leads share one participant record, but you can run either on its own.
Your programs at a glance, a scored outreach-health view per study with a plain-language progress summary, every named partner engaged on your study, and referrals as they come in — updating live, not in a weekly deck.
Log in to your Bridge portal to see live progress, or talk to our team about standing up outreach for a new study.
Prefer email? info@bridge-by-clinicontact.com